How the anion gap Measures
The anion gap is a practical way to gauge the relationship between recorded cations and observed anions in blood tests. In routine use, it helps clinicians detect the presence of additional anions and better understand a patient’s acid-base status. The calculation is built from routine lab values on an electrolyte test panel, especially sodium, chloride, and blood bicarbonate.
At a simple level, the concept reflects charge balance: the body’s different charges should remain equal. Because not all ions are directly measured, the anion gap functions as an indirect marker of hidden acids or other charged particles. That is why it has become such an important diagnostic tool in acid-base regulation and clinical assessment.
The usual calculation formula is:
Anion gap = Serum sodium - (Serum chloride + Serum bicarbonate)
Some clinicians use alternative equations depending on local practice, but the underlying purpose is the same: to assess whether there are excess acids in the blood that are not reflected in the standard blood electrolytes. This matters most when evaluating metabolic acidemia, where the pattern can point toward high anion gap metabolic acidosis or non-anion gap metabolic acidosis.
Understanding the meaning of the anion gap is not just about memorizing a number. It is about linking the result to the patient’s overall presentation, the likely disease process, and the broader diagnostic strategy. In practice, the anion gap interpretation becomes one piece of a larger acid-base interpretation.
How to Work With an Anion Gap Calculator
An anion gap calculator simplifies the calculation formula, but it still requires accurate input and deliberate interpretation. To use it successfully, enter the patient’s serum sodium, serum chloride, and serum bicarbonate from the very same blood draw whenever possible. Slight changes in timing or specimen handling can affect the result and change the impression of acid-base disorders.
Many calculators also ask for albumin because low protein levels can make the measured gap appear falsely normal. This is where albumin correction becomes essential. An albumin-corrected anion gap helps detect hidden high-gap states that might otherwise be missed, especially in patients with chronic illness or poor nutritional status.
When using the calculator, keep the expected reference range in mind. The normal range varies depending on the laboratory method and whether potassium is included in the equation. A result should never be viewed in isolation. The number must be interpreted in the context of the patient’s symptoms, acid-base pattern, and other chemistry findings.
For the most useful interpretation, think of the calculator as a bridge between data and diagnosis. It can identify whether the patient may have an elevated gap, but it does not explain why. That step requires integration with pH, carbon dioxide levels, clinical findings, and the likely source of acid gain or bicarbonate loss.
In practical terms, the best use of an anion gap calculator is to support early recognition of hidden acid disorders, guide next steps in testing, and sharpen the differential diagnosis. It is especially valuable when a patient’s serum electrolytes do not neatly fit a single pattern.
Stepwise Analysis of the Anion Gap
Interpreting the anion gap begins with establishing whether the patient has acidemia from metabolism. If the bicarbonate is low and the pH is acidemic, the next step is to determine whether the case is a increased anion gap condition or a non elevated anion gap condition. This separation limits the differential diagnosis and guides the rest of the workup.
Step one is to calculate the gap from the measured electrolyte values. The second step is to compare that result with the laboratory’s reference range. If the gap is elevated, the body likely contains additional acids represented by undetected anions. If the gap is normal, bicarbonate loss or chloride gain is more likely than accumulation of unmeasured acids.
In high anion gap metabolic acidosis, the extra acid consumes bicarbonate while leaving behind ions that are not routinely measured. Common examples include lactic acidosis, ketone-related acidosis, kidney failure, and toxic substances. In contrast, non elevated anion gap metabolic acidosis often reflects bicarbonate loss through the gastrointestinal tract or kidneys, with loose stools being a classic cause.
The third step is to assess whether the numbers fit the clinical picture. A patient with severe illness, low bicarbonate, and a modestly elevated gap may still have an important acid burden. A patient with a normal gap does not automatically have a benign process. The key is clinical judgment, not just numeric confirmation.
Step four is to look for patterns that suggest more than one disorder at once. That is where the anion gap becomes especially powerful. A single patient may have both a high-gap acidosis and a normal-gap acidosis, or an acidosis plus a respiratory disorder. These combinations are common in real-world acid-base evaluation.
Detecting mixed acid-base disorders
A mixed acid-base disorder occurs when several primary process affects the pH at the same point in time. This is a crucial concept because the anion gap can reveal hidden complexity that a single pH value might miss. The patient may have a metabolic disorder plus compensatory respiratory change, or two primary disorders acting in opposite directions.

Another useful method is the delta gap. It compares the rise in anion gap above normal to the fall in bicarbonate below normal. If the rise in the gap is larger than the fall in bicarbonate, a concurrent metabolic alkalosis may exist. If bicarbonate falls more than expected for the rise in the gap, there may be an additional normal-gap acidosis.
The delta-delta ratio builds on that logic. It assists in determining whether the change in the anion gap and the change in bicarbonate change in a balanced way. A low ratio can suggest a combined high-gap and normal-gap metabolic acidosis, while a high ratio can suggest a mixed disorder involving metabolic alkalosis. This type of analysis is especially helpful when the patient has multiple potential causes of acid-base disturbance.
Respiratory status must also be evaluated. Respiratory compensation should show a predictable pattern when a metabolic disorder is primary. If the carbon dioxide level is not appropriate for the degree of acidosis, then a concurrent respiratory alkalosis or acidotic respiratory disorder may be present. That means the pH, bicarbonate, and carbon dioxide must all be interpreted together.
For example, a patient with diabetic ketoacidosis may also have vomiting, creating a metabolic alkalosis that partially masks the severity of the acidosis. Another patient with renal failure may have a high-gap acidosis along with chronic respiratory compensation. Recognizing these overlapping patterns is the difference between basic calculation and advanced clinical reasoning.
Common Causes of Increased and Normal Anion Gap
The diagnostic differential varies depending on whether the anion gap is high or normal. In elevated anion gap metabolic acidosis, the leading causes include lactic acidosis, ketoacidosis, renal failure, and toxins. These disorders raise the concentration of organic acids or other unmeasured acids in the bloodstream.
Lactic acidosis often reflects tissue hypoperfusion, severe infection, hypoxia, or impaired lactate clearance. Ketoacidosis can occur with diabetes, prolonged fasting, or alcohol-related metabolic states. Renal failure causes accumulation of acids that the kidneys can no longer excrete efficiently. Toxins may produce a high gap by forming or introducing acids that disrupt normal metabolism.
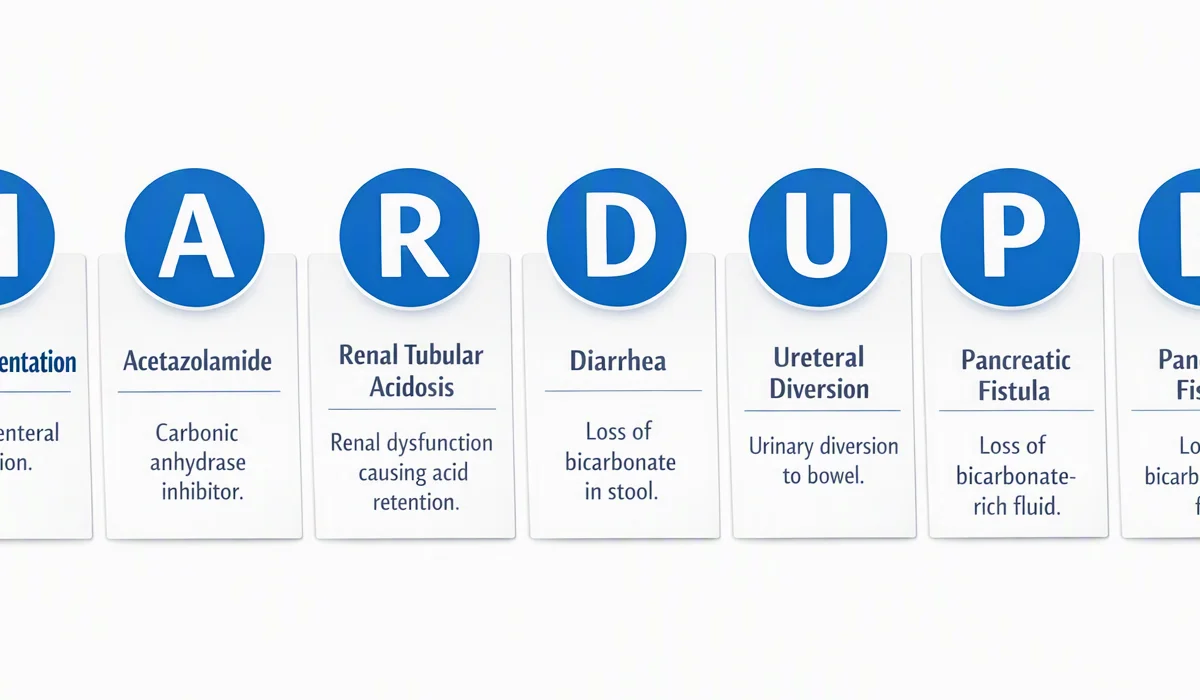
In normal anion gap metabolic acidosis, the issue is often bicarbonate loss or chloride retention. Diarrhea is a classic cause because bicarbonate-rich intestinal fluid is lost from the body. Other mechanisms include renal tubular defects or other states where acid is retained without a net increase in unmeasured anions.
It is useful to think in terms of pattern recognition. High-gap states usually imply hidden acid accumulation. Normal-gap states more often imply a replacement of bicarbonate by chloride. That distinction helps guide clinical interpretation and focuses attention on the most likely source of the disorder.
Sometimes a patient has both. For example, severe diarrhea plus lactic acidosis can create a mixed acid-base disorder with features of both normal-gap and high-gap acidosis. That is why the anion gap should always be interpreted as part of a broader diagnostic approach.
Albumin Correction and Why It Matters
Albumin is a significant unmeasured negative ion, so it has a clear effect on the measured gap. When hypoalbuminemia is present, the apparent anion gap may be reduced than expected even if significant acid accumulation exists. This can lead to missed recognition of a high-gap disorder unless an albumin-corrected anion gap is calculated.
The purpose of albumin correction is to modify the result so it better reflects the actual acid burden. In practical terms, a low serum albumin can conceal elevated unmeasured anions. Correcting for albumin helps bring back the usefulness of the gap as a marker of acid-base disturbance.
This matters in patients with chronic illness, inflammation, malnutrition, liver disease, or fluid shifts, where albumin may be decreased. Without correction, the raw number may look reassuring even when the patient has clinically important metabolic acidosis. The corrected values often show a more accurate picture of acid-base status.
It is also important to consider measurement error. Albumin assays, electrolyte measurements, and specimen handling issues can all affect the final result. A corrected calculation is valuable, but it should still be viewed alongside the overall clinical context.
In summary, albumin correction improves anion gap interpretation by accounting for a major source of variation. It does not replace clinical judgment, but it often avoids missed diagnoses and helps distinguish true normal-gap states from masked high-gap states.
Common Pitfalls and Ways to Avoid Them
A frequent mistake in lab interpretation is using the anion gap as a standalone diagnosis. It is only one part of acid-base analysis. A result that seems normal can be misleading if albumin is low, if there is electrolyte imbalance, or if another disorder is modifying the expected pattern.
Another problem is overlooking mixed disorders. A patient may appear to have a straightforward metabolic acidosis, but the actual picture may include respiratory compensation, respiratory alkalosis, or respiratory acidosis. Failing to check the carbon dioxide response can lead to incomplete or incorrect interpretation.
Excessive reliance on a single cut-off can also cause errors. The reference range varies by lab, method, and whether potassium is included. This is why the result should always be read in relation to the institution’s standard and the patient’s clinical correlation. A borderline value may still be important if the overall presentation suggests a more serious disorder.
A further mistake is ignoring the broader physiology. A patient with sepsis, shock, or organ failure may have multiple drivers of acidosis. In that setting, the gap helps identify the presence of unmeasured anions, but it does not identify the whole cause. The full picture requires history, examination, imaging when appropriate, and repeated laboratory assessment.
To avoid mistakes, use the anion gap as a structured framework:

- Make sure the patient has an acid-base problem. Calculate the gap from serum sodium, serum chloride, and serum bicarbonate. Review whether albumin is low and apply an albumin-corrected anion gap. Look for high anion gap metabolic acidosis versus normal anion gap metabolic acidosis. Look for a mixed acid-base disorder using the delta gap and delta-delta ratio. Verify respiratory compensation and compare with the expected pattern. Integrate the numbers with the patient’s symptoms, history, and likely cause.
This stepwise process improves clinical interpretation and reduces the chance of missing important disease. The best anion gap calculator workflow is not https://anion-gap-values582.quantlynix.com/posts/anion-gap-calculator-based-on-serum-chloride just numeric; it is a structured process to diagnosis.
FAQs About the Anion Gap Calculator
What is an anion gap calculator used for?
An anion gap calculator is employed to estimate the anion gap from serum sodium, serum chloride, and serum bicarbonate. It assists clinicians identify high anion gap metabolic acidosis, assess normal anion gap metabolic acidosis, and guide broader acid-base analysis in patients with suspected acid-base disorders.
How do you calculate the anion gap in mixed acid-base disorders?
Use the standard calculation formula: serum sodium minus the sum of serum chloride and serum bicarbonate. Then read the result in context. In a mixed acid-base disorder, the delta gap and delta-delta ratio can help determine whether more than one metabolic process is present, while respiratory compensation helps to reveal any concurrent respiratory disorder.
Why should the anion gap be corrected for albumin?
Albumin is a major unmeasured anion, so low levels can make the gap seem falsely normal. An albumin-corrected anion gap increases accuracy in patients with hypoalbuminemia and can uncover hidden acid accumulation that might otherwise be missed. This correction improves anion gap interpretation and reduces diagnostic error.
What does a high anion gap mean clinically?
A high anion gap usually means there are excess unmeasured anions in the blood, often from lactic acidosis, ketoacidosis, renal failure, or toxins. Clinically, it suggests a form of metabolic acidosis that needs prompt evaluation. The finding is important, but it should always be interpreted with the full clinical picture and the patient’s overall acid-base status.
How do you recognize if a patient has a mixed acid-base disorder?
Look for results that fail to match a single consistent pattern. Compare the pH, bicarbonate, and carbon dioxide with the expected pattern of respiratory compensation. After that use the delta gap and delta-delta ratio to check whether the changes in anion gap and bicarbonate reflect a single process. If they do not, a mixed acid-base disorder is likely and further diagnostic approach is needed.