An Anion Gap Calculator is a practical aid for interpreting an anion gap result on a metabolic panel. It aids in translate common laboratory values into a reliable diagnostic clue for reviewing acid-base balance, especially when a clinician is reviewing an electrolyte panel for signs of metabolic acidosis or related acid-base disorder patterns.
When used properly, the calculator does far more than produce a number. It helps link serum sodium, serum chloride, and serum bicarbonate to the broader picture of metabolic panel interpretation. That means it can aid recognition of a high anion gap, a low anion gap, or results that need confirmation with additional testing.
Explaining the Anion Gap Indicates
The anion gap is an estimate of the gap between measured positively charged and negative electrolytes in the blood. In routine practice, it mainly describes the relationship between sodium, chloride, and bicarbonate. Because not all electrically charged particles are directly measured, the anion gap provides an indirect look at the presence of unmeasured ions and unmeasured anions.
In simple terms, the anion gap helps reveal whether something is affecting acid-base balance. A normal result suggests that the measured cations and anions are in usual ratio, while an abnormal result may suggest an underlying acid-base disorder. This is why the anion gap is a standard part of metabolic panel interpretation in many settings.
Although the number is derived from routine chemistry tests, its clinical significance is much broader than the formula itself. A change in the anion gap can be a diagnostic clue that triggers a more detailed metabolic acidosis evaluation, review of medications, or follow-up testing such as a blood gas.
How to Work Out the Anion Gap
An Anion Gap Calculator simplifies the process of calculate anion gap from findings from a basic metabolic panel or comprehensive metabolic panel. The most widely used anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Some labs may use small variations of formulas, especially if potassium is included. But, the sodium-based version is the most common in everyday interpretation.
To use the calculator, enter the patient’s serum sodium, serum chloride, and serum bicarbonate. The result estimates the gap between measured cations and anions. If the number is higher than expected, it may indicate extra unmeasured anions. If it is lower than expected, the result may reflect low albumin, lab variation, or another less common cause.
The calculator is especially helpful when reviewing a electrolyte panel rapidly. For example, a low bicarbonate with normal chloride may raise suspicion for metabolic acidosis, while a low bicarbonate with a markedly elevated anion gap suggests a high gap acidosis.
It is important to remember that the calculator is only one step in clinical reasoning. It assists, but does not replace, a full assessment of symptoms, history, medications, and the rest of the lab pattern.
Normal Anion Gap Ranges and What Affects Them
The expected range for the anion gap varies with the assay method and the lab’s normal interval or lab reference range. Because different laboratories measure ions differently, a result that is “normal” in one setting may sit slightly outside the range used elsewhere.
Such differences is one reason clinicians should always interpret the number in context rather than relying on a single cutoff. The lab’s stated normal range is the most useful guide for that specific result.
Albumin has a major effect on the anion gap because it is a negatively charged protein and contributes substantially to the pool of unmeasured anions. When albumin is low, the anion gap may appear falsely reduced even if an acid-base problem is present. This is where albumin correction becomes important.
An corrected-for-albumin or albumin-corrected anion gap estimate adjusts for low albumin so the result better reflects the true acid-base picture. In practical terms, if albumin is low, the corrected value may reveal a hidden elevation that would otherwise be missed. This helps reduce the risk of a falsely low anion gap.
Albumin adjustment is especially helpful when the patient has illness, inflammation, malnutrition, liver disease, or fluid overload—situations where albumin may be below the usual range. In those cases, the raw result may not fully represent the patient’s actual acid-base status.
High Anion Gap Metabolic Acidosis Causes
A high anion gap is frequently associated with metabolic acidosis. This takes place when acids accumulate in the blood and boost the amount of unmeasured anions. The bicarbonate level frequently falls because it is being used to buffer acid, and the anion gap rises as a result.
Frequent causes of high anion gap include:
- Lactate buildup, which can occur when tissues are poorly perfused or under severe metabolic stress Ketone-related acidosis, including diabetic or alcoholic forms Kidney failure, where the kidneys cannot eliminate acid effectively Exposure to certain toxins or drugs that generate or hold onto acids
Lactate buildup is a common cause of increased gap results and frequently signals tissue hypoxia, sepsis, or other conditions that reduce oxygen delivery or utilization. Ketone-related acidosis usually appears with increased ketones and may be seen in diabetes, prolonged fasting, or heavy alcohol use. Renal failure contributes by reducing acid excretion and allowing acid metabolites to build up.
When the calculator returns a high value, the next step is not just to label it unusual. The key is to relate it to the patient’s overall clinical picture. For example, a low bicarbonate with a high anion gap strongly supports a high anion gap acidosis pattern, but the exact cause still requires targeted evaluation.
In many cases, the anion gap is a starting point for a systematic workup. Depending on the context, that may include lactate, ketones, creatinine, toxicology testing, and a arterial blood gas to assess pH and compensation.
Decreased Anion Gap Reasons and Clinical Importance
A decreased anion gap is less common than a high one, but it can be important clinically. The most common explanation is hypoalbuminemia, since albumin is a major unmeasured anion. When albumin falls, the measured gap may drop even if the patient’s acid-base status is otherwise unchanged.
Other important causes include multiple myeloma, lithium exposure, and paraproteinemia. These conditions can lower the calculated gap by adding positively charged proteins or cations into the system, altering the balance of measurable ions.
Multiple myeloma and other paraproteinemia states can produce abnormal proteins that influence the result. This is why an unexpectedly low number should not be ignored automatically. It can be a clue to a broader diagnostic process, especially if the patient also has anemia, kidney dysfunction, bone pain, or elevated total protein.
Lithium is an additional notable cause because it is a cation that can affect the calculation. In the right clinical setting, a low anion gap may provide an earliest https://anion-gap-guide797.opalvector.com/posts/can-hypermagnesemia-lower-the-anion-gap-2 warning sign of lithium effect or toxicity.
As with a high result, a low value requires clinical context. A low gap may be due to true disease, but it can also reflect a measurement issue or a misleading result from low albumin. Adjusting for albumin and reviewing the full chemistry panel improves interpretation.
Interpreting Results for a Metabolic Panel
Effective interpretation of metabolic panels begins with the overall picture, not the number alone. The anion gap should be reviewed alongside acid-base balance, sodium, chloride, bicarbonate, and the patient’s overall condition. A complete interpretation often reveals whether the problem is an electrolyte disturbance, an acid accumulation state, or a combination of both.
As an example, a low bicarbonate with elevated chloride may indicate a normal-gap acidosis with a shift in chloride. In that scenario, the body may be exchanging bicarbonate loss for chloride gain, keeping the anion gap within range even though acidosis is present. By contrast, low bicarbonate with a high anion gap points more toward acid accumulation from causes such as lactic acidosis, ketoacidosis, or renal failure.
The chloride change is important because chloride often rises as bicarbonate falls in certain forms of acidosis. That means a patient can have clear acid-base disruption even when the anion gap is not elevated. This is why the calculator should be used as part of a broader review of the entire electrolyte profile.
One useful approach is to interpret results in this order:

- Check sodium, chloride, and bicarbonate for readily seen abnormalities Use the Anion Gap Calculator to identify a high or low pattern Assess whether albumin may require correction Compare the pattern with likely causes and symptoms Determine whether additional testing, including a blood gas, is needed
This method improves the chance of identifying the correct acid-base disorder and makes the result more useful than a standalone calculation. The anion gap is best viewed as a useful bridge between raw lab values and a diagnosis that explains what is happening physiologically.
Drawbacks, Common issues, and When to Retest
Despite this a properly used calculator has constraints. One important issue is laboratory error. A specimen problem, sample contamination, or analyzer issue can produce a misleading value. When the number does not fit the clinical picture, a repeat test is often the best next step.
Another pitfall is failure to account for hidden anions or protein-related effects. If albumin is low, the raw number may underestimate the severity of the underlying disturbance. If a patient has abnormal proteins or unusual cation exposure, the result may be shifted in the opposite direction.
A arterial blood gas can be useful when the chemistry panel and symptoms do not align. It provides pH and respiratory compensation data, which can clarify whether the issue is truly metabolic, respiratory, or mixed. In patients with severe illness, the blood gas may also help confirm the urgency of the finding.
Recheck the result when:
- The value does not match with the patient’s condition There may have been sample mishandling Albumin is not normal and correction has not been applied There is suspicion for a hidden acid-base problem Therapy has begun and response needs confirmation
In short, the calculator is valuable, but it should not be treated as the final answer. A careful recheck can prevent misclassification and help distinguish a true abnormality from a transient or artifactual finding.
FAQ
What is an Anion Gap Calculator used for?
An Anion Gap Calculator is used to help interpret a metabolic panel by estimating the difference between measured electrolytes and identifying possible acid-base abnormalities. It is especially helpful for spotting a high anion gap or decreased anion gap pattern and for guiding next-step clinical reasoning.
How do you calculate the anion gap from a metabolic panel?
The standard formula for the anion gap is sodium - (chloride + bicarbonate). This calculation uses values from a basic metabolic panel or comprehensive metabolic panel. Many clinicians use a calculator to make this faster and reduce arithmetic errors.
How to understand a normal anion gap range?
The normal reference range can vary by lab because different instruments and methods can shift the result. That is why you should use the lab’s stated normal range or laboratory reference range rather than choosing one standard cutoff.
What causes the anion gap be high or low?
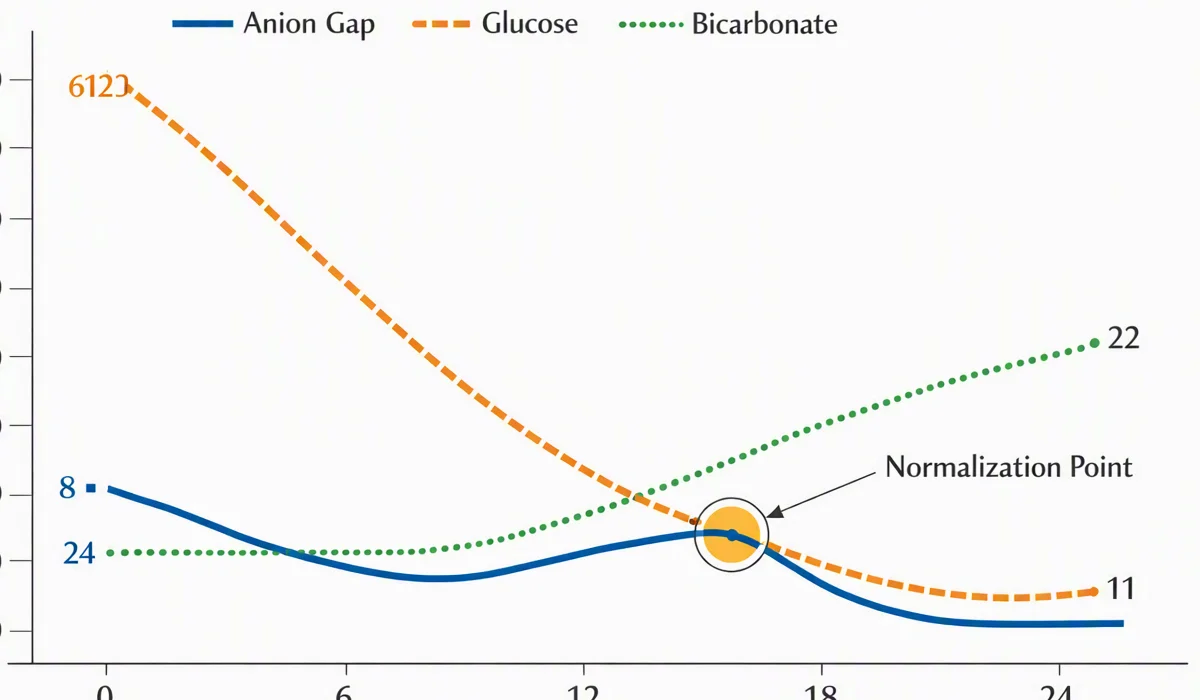
A raised anion gap often suggests metabolic acidosis from causes such as elevated lactate, ketone-related acidosis, or kidney failure. A reduced anion gap is often linked to low albumin, but it can also occur with multiple myeloma, lithium use, or abnormal proteins in the blood.
Should albumin be corrected when interpreting the anion gap?
Yes, it should, when serum albumin is low, correction for albumin can improve interpretation and reveal a more accurate corrected anion gap. This is significant because reduced albumin can make the gap look lower than it really is, leading to a false low anion gap and a missed diagnostic clue.